

In the documentary feature film “Complicated,” viewers get a real life look at how medical complexity interferes with healthcare access for children and young people with connective tissue disorders, even in top hospital systems.
One of the main complexities chronicled over the nine years of filming “Complicated” is neurological illness and decline in young people. Audiences witness Morgan’s heartbreaking and unexpected psychological deterioration as the film highlights how limitations in medical testing and diagnosis can often leave the underlying cause of psychological illness unidentified. Unfortunately this outcome is common. [1]
Many parents can empathize with Morgan’s mother Laurie, trying to advocate for her daughter by explaining, “she is getting worse, she is getting worse, she is getting worse,” only to discover her daughter is being discharged from treatment and sent home the next day. Families are often left to navigate the overwhelming ‘no man’s land’ that exists when a person has medical complexity AND complicated psychological illness.
Karen, another vibrant young woman in the film, fights hard for life, accepting difficult interventions that will enable her to get back to living. Her resilience and determination often masks just how sick she really feels and really is. [2] To see someone so young, dealing with so many serious symptoms, perhaps it is understandable why some physicians tragically struggled to believe how ill she really was and were quick to dismiss her symptoms as psychological.
As both young women journeyed from specialist to specialist, physicians focused on symptoms, but what about the bigger question that really needed to be asked and answered?
Why would neurological illness occur in a teenager?
Recent research sampling urine, blood and tissue after death in six chronically ill young people who committed suicide or had suicidal ideations found something strange. Five of these youth had in their bodies, the DNA of Babesia, a microscopic parasite that is spread by black legged ticks, and the DNA of Bartonella henselae, the bacteria caused by cat scratch disease spread by cats carrying infected flea waste. [3]
What is happening?
What is happening? As microbiologist and science communication director at the Brain Inflammation Collaborative, Matthew Menendez, points out, “Everyone has experienced inflammation that alters their behavior at some point in their lives whether they realize it or not. For instance, the inflammation from an acute viral infection tells your brain to rest so the excess energy can be redirected to the immune system, helping you recover from the infection.”
Yet could infections be more important in the causes of many neurological and neuropsychiatric illnesses than we realize? What puts the central nervous system at risk? [4] Is something happening to people where the normal protections of the central nervous system are breached?
Normal protections of the central nervous system (CNS)
The central nervous system, our brain and spinal cord, is protected by bone, the three layers of meninges, cerebral spinal fluid (CSF) and most importantly, the blood brain barrier (BBB).
What is the BBB?
This barrier tightly controls what passes from the bloodstream into the brain and spinal cord environment. The BBB keeps what is in the blood out of the brain. Endothelial cells line the inside of the blood vessels but these are specialized endothelial cells called brain microvascular endothelial cells (BMEC). These cells lie on an 80-nm thick unique type of extracellular matrix layer (ECM), surrounded by pericytes (cells involved in blood flow and in forming new blood vessels) and astrocytes (cells involved in supplying nourishment to and protection of nerves). [5]
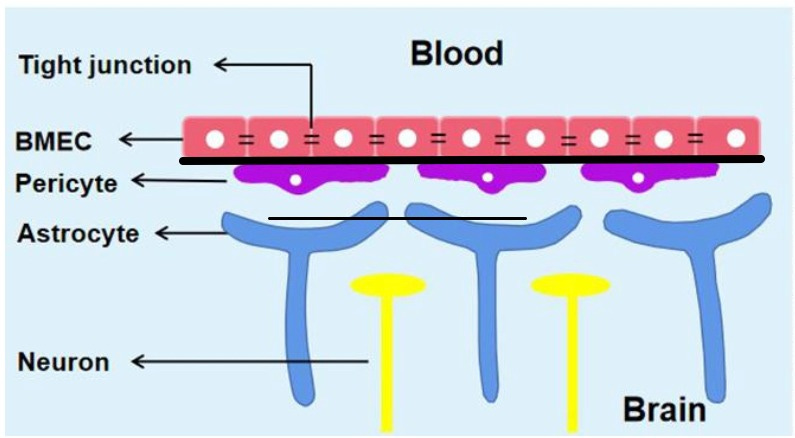
The dark line in figure above represents the ECM.
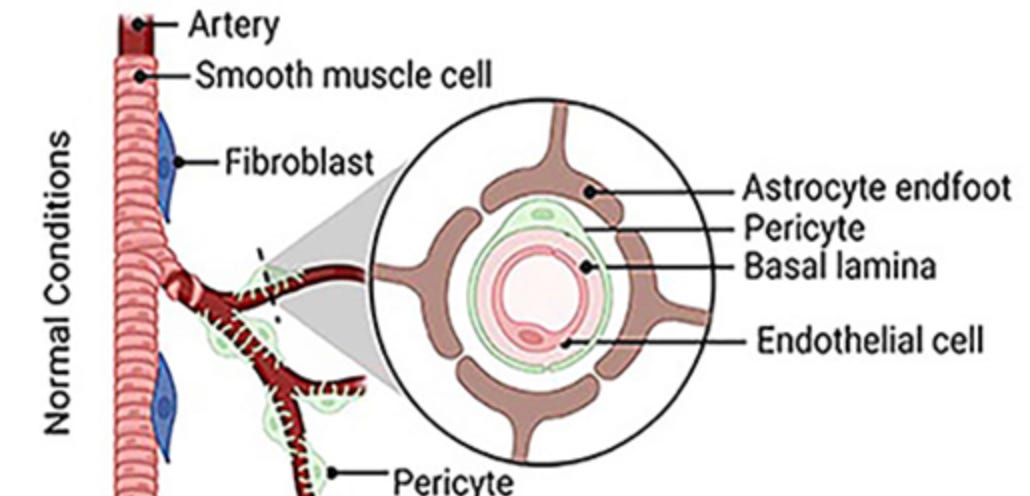
14) https://pmc.ncbi.nlm.nih.gov/articles/PMC9769996/
The Extracellular Matrix (ECM) Layer
The most common cells of connective tissue are fibroblasts. Fibroblasts ,along with endothelial cells, secrete the combination of proteins, water and complex sugars that make collagens, elastin, and laminin, among other stringy materials that are the extracellular matrix (ECM). Connective tissue is primarily ECM. [6, 7]
The ECM used to be thought of as inactive and passive, something that just provided strength to organs and tissues. Now it is understood as bioactive, something that interacts with cells, signaling them and controlling their behaviors for example, migration (movement) and differentiation (changing into other cells). This shift in understanding of the ECM, changes everything.
Now we know that, in the brain, the ECM controls the tight junctions between the endothelial cells, acting as selective barriers.
[8]https://doi.org/10.1128/cmr.00118-13
How do microbes enter the brain?
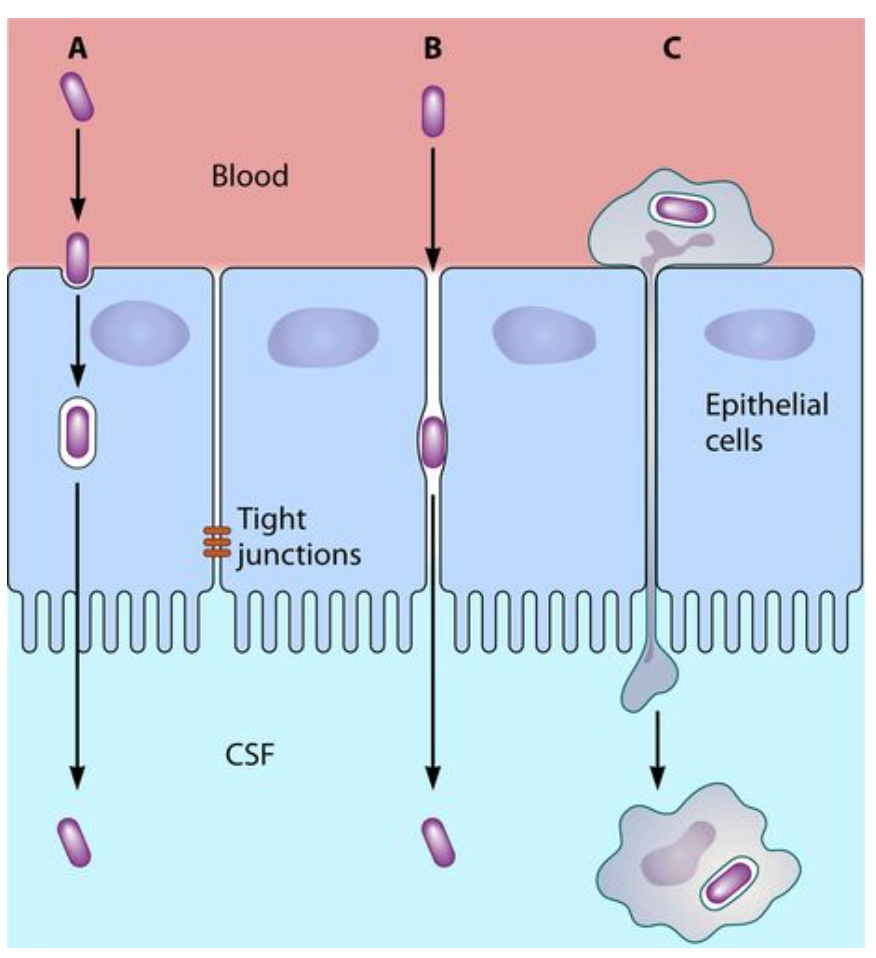
There are three ways that microbes can sneak into the central nervous system. One is by actually transporting through the endothelial cells of the blood vessels. (A in the above image) This is done by having receptors on the microbes’ surface that match the receptors on the endothelial cells’ surface and actually going through the cell unscathed. This is how SARS Covid 19 enters the brain.
Another is by disrupting the tight junctions (B) or finding disruptions in the tight junctions between endothelial cells.
Microglia are the immune cells of the brain. So, neutrophils, B cells, T cells, and monocytes, the white blood cell powerhouses of the immune system in the rest of the body, are not normally allowed in the brain by the BBB. But the third way microbes slip through the barriers (C) is a kind of “trojan horse” strategy where infected white blood cells actually carry the microbe between endothelial cells. Both strategy B and C seem to require some type of breakdown in the ECM since it is in charge of tight junctions.
ECM Disruption
How does this occur? Mast cells may contribute to microbes accessing the brain. Mast cells live in connective tissue and are on the brain side of the BBB. These immune cells are part of what is called the innate immune system and are the body’s first line of defense against allergens, bacteria, viruses, fungi, parasites and other invaders that can cause disease. [9]
Mast cells get their marching orders from B cells. B cells are white blood cells (lymphocytes) that produce antibodies (another name for an antibody is immunoglobulin). Even though the B cells are too large to get through the BBB, their antibodies/immunoglobulin can. The type that activates mast cells is called Immunoglobulin E (IgE).
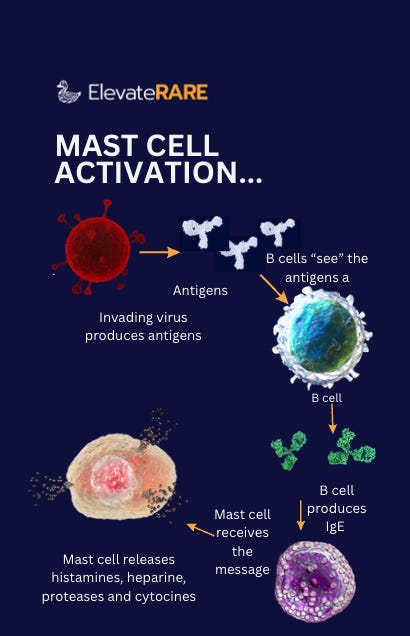
When B cells encounter chemicals (called antigen) produced by foreign invaders, they release IgE. IgE latches onto mast cell receptors on their surfaces and activates the release of histamines and other chemicals in the granules located throughout the mast cells’ cytoplasm. Mast cells degrade the ECM with those chemicals, especially heparin, histamine, serotonin, nitric oxide and cytokines like TNF-a. [10,11,12, 13] TNF-a is a cytokine that opens the tight junctions of the BBB and allows white blood cells from the bloodstream to enter the brain.
There are a number of microbes that are known to breach the BBB.
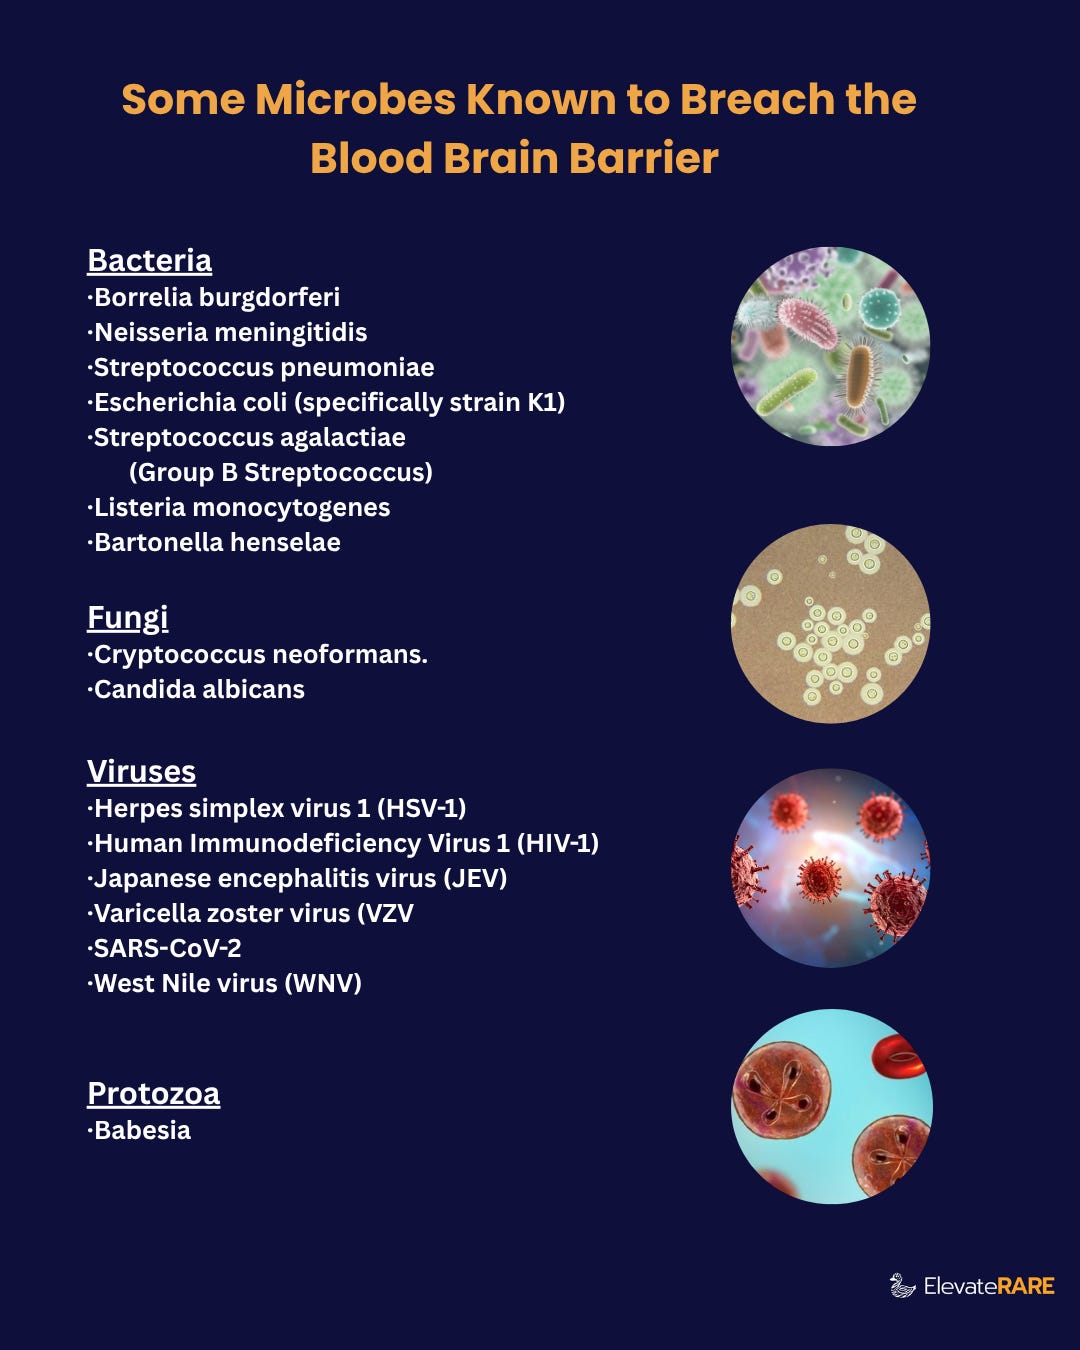
There are also the streptococcus bacteria in Group A, the ones that cause strep throat, which increase BBB permeability and inflammation. The PANS (Pediatric Acute-onset Neuropsychiatric Syndrome) and PANDAS (Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal Infections) result from exposure to these bacteria.
As can be seen, microbes can evade the BBB even when people have normal connective tissue. What happens when people have defective collagen and associated comorbid disorders like Mast Cell Activation Disorder.
What happens when ECM in the brain is made of defective collagen?
The answer is that the BBB is not as effective a barrier for them. These people are the canaries in the mineshaft.
Mounting evidence reveals that infections from microbes can cause neurological symptoms in people with defective collagen. [3] Significant amounts of research on the symptoms of people with hypermobile Ehlers-Danlos Syndrome (hEDS), reveal neurological symptoms including fatigue, pain, headache, migraine, neuropsychiatric illnesses, CSF leaks, and poor circulation. [4, 15, 16]
Intravenous immunoglobulin (IVIG) a blood product prepared from the serum of pooled antibodies from between 1,000 and 15,000 donors per batch, treats overactive immune systems, fights severe infections and treats immune deficiencies. Neurology, hematology, immunology, nephrology, rheumatology and dermatology all utilize this vital treatment for Guillain Barre syndrome, immune thrombocytopenia, Kawasaki syndrome, post bone marrow transplant, PANDAS and systemic lupus erythematosus to name a few.[17]
Sadly, accessing IVIG for PANS and PANDAS has been difficult for many, despite families seeing improvements in their loved ones’ quality of life. They report delays and denials from insurance companies and many experience increased financial burden. [17, 18]
An Unexpected Finding
After Karen’s death, her autopsy revealed Alzheimer’s-type 2 neuropathology at an age when no one would have expected to find it. That discovery should prompt questions about why. [2] Factors like infection, immune dysregulation and connective tissue need to be considered.
How many other patients are carrying a microbial condition causing neurological disease that is being mistaken for psychiatric illness because we have not yet learned what to look for?
Call for more research
Clinicians and researchers should be more curious about these findings. Psychological symptoms, neurological decline, chronic pain, cognitive challenges and other symptoms that have all too often been misdiagnosed as “all in your head” may well be caused by inflammation, immune dysfunction, infections or other biological disease processes that science is only just beginning to understand.
Christy Jagdfeld, CEO of the Brain Inflammation Collaborative put it this way, “We must break down diagnostic silos and accelerate research across the entire spectrum of neuroinflammatory and post-infectious illnesses. Complex chronic conditions—such as EDS, POTS, MCAS, chronic Lyme and others—share deeply overlapping biological pathways that traditional medicine too often treats in isolation or as psychological issues. Expanded, collaborative research across all of these diagnoses is urgently needed to replace years of diagnostic delay with clear biological validation.”***
In Complicated, Morgan’s symptoms were repeatedly interpreted through a psychological lens while her physical illness continued to progress. That story is not unique. It reflects what countless patients’ and families’ experiences every day when medicine reaches the limits of its current understanding.
Morgan and Karen are just two reasons why it might be time to rethink how psychological diagnoses are made.
This is not just a scientific question. It is a human one.
*** The Brain Inflammation Collaborative is conducting research, gathering cross-condition, real-world evidence to uncover the root mechanisms.
References
1) Abrahams A. Sullivan D. Complicated [Video]. Culver City, California: Apple, Inc; 2026.
2) Shirvani A, Shirvani P, Jonah U, Moore BE, Holick MF. Suspected Mitochondrial Dysfunction and Complex Pathophysiology in Fatal Hypermobile Ehlers–Danlos Syndrome: Insights from a Case Report and Post-Mortem Findings. Biomedicines. 2025; 13(2):469. https://doi.org/10.3390/biomedicines13020469
3) Breitschwerdt, E.B., Robveille, C., Maggi, R.G. et al. Postmortem evidence of Babesia and Bartonella infections in chronically ill suicidal young people. Parasites Vectors (2026). https://doi.org/10.1186/s13071-026-07541-8
4) Severance S, Daylor V, Petrucci T, Gensemer C, Patel S and Norris RA (2024) Hypermobile Ehlers-Danlos syndrome and spontaneous CSF leaks: the connective tissue conundrum. Front. Neurol. 15:1452409. doi: 10.3389/fneur.2024.1452409
5) Félétou M. The Endothelium: Part 1: Multiple Functions of the Endothelial Cells—Focus on Endothelium-Derived Vasoactive Mediators. San Rafael (CA): Morgan & Claypool Life Sciences; 2011. Chapter 1, Introduction. Available from: https://www.ncbi.nlm.nih.gov/books/NBK57145/
6) McKee, T.J., Perlman, G., Morris, M. et al. Extracellular matrix composition of connective tissues: a systematic review and meta-analysis. Sci Rep 9, 10542 (2019). doi.org/10.1038/s41598-019-46896-0]
7) Järveläinen H, Sainio A, Koulu M, Wight TN, Penttinen R. Extracellular matrix molecules: potential targets in pharmacotherapy. Pharmacol Rev. 2009 Jun;61(2):198-223. doi: 10.1124/pr.109.001289.
8) Dando SJ, Mackay-Sim A, Norton R, Currie BJ, St. John JA, Ekberg JAKBatzloff M, Ulett GC, Beacham IR 2014. Pathogens Penetrating the Central Nervous System: Infection Pathways and the Cellular and Molecular Mechanisms of Invasion. Clin Microbiol Rev 27:. https://doi.org/10.1128/cmr.00118-13
9) Johnson D, Krenger W. Interactions of mast cells with the nervous system – recent advances. Neurochem Res. 1992;17:939–51. doi: 10.1007/BF00993271. ]
10) Silverman AJ, Sutherland AK, Wilhelm M, Silver R. Mast cells migrate from blood to brain. J Neurosci. 2000;20:401–8. doi: 10.1523/JNEUROSCI.20-01-00401.2000. ]
11) Brown MA, Hatfield JK. Mast Cells are Important Modifiers of Autoimmune Disease: With so Much Evidence, Why is There Still Controversy? Front Immunol. 2012;3:147. doi: 10.3389/fimmu.2012.00147.
12) Lindsberg PJ, Strbian D, Karjalainen-Lindsberg ML. Mast cells as early responders in the regulation of acute blood-brain barrier changes after cerebral ischemia and hemorrhage. J Cereb Blood Flow Metab. 2010;30:689–702. doi: 10.1038/jcbfm.2009.282.
13) Nelissen S, Lemmens E, Geurts N, et al. The role of mast cells in neuroinflammation. Acta Neuropathol. 2013;125:637–50. doi: 10.1007/s00401-013-1092-y
14) Xu L, Nirwane A, Xu T, Kang M, Devasani K, Yao Y. Fibroblasts repair blood-brain barrier damage and hemorrhagic brain injury via TIMP2. Cell Rep. 2022 Nov 22;41(8):111709. doi: 10.1016/j.celrep.2022.111709.
15) Bendik EM Tinkle BT Al-shuik E Levin L Martin A Thaler R et al. Joint hypermobility syndrome: a common clinical disorder associated with migraine in women. Cephalalgia. (2011) 31:603–13. doi: 10.1177/0333102410392606
16) SchievinkWI. Spontaneous spinal cerebrospinal fluid leaks and intracranial hypotension. JAMA. (2006) 295:2286–96. doi: 10.1001/jama.295.19.2286
17) Jolles S, Sewell WA, Misbah SA. Clinical uses of intravenous immunoglobulin. Clin Exp Immunol. 2005 Oct;142(1):1-11. doi: 10.1111/j.1365-2249.2005.02834.x.
18) Calaprice, et al. Access to Care in Pediatric Acute-Onset Neuropsychiatric Syndrome: A Survey of Families’ Journeys to and Experiences with Intravenous Immunoglobulin Treatment. Journal of Child and Adolescent Psychopharmacology Volume 36, Issue 4. doi.org/10.1177/10445463261440137

Very cool and well explained, thank you.